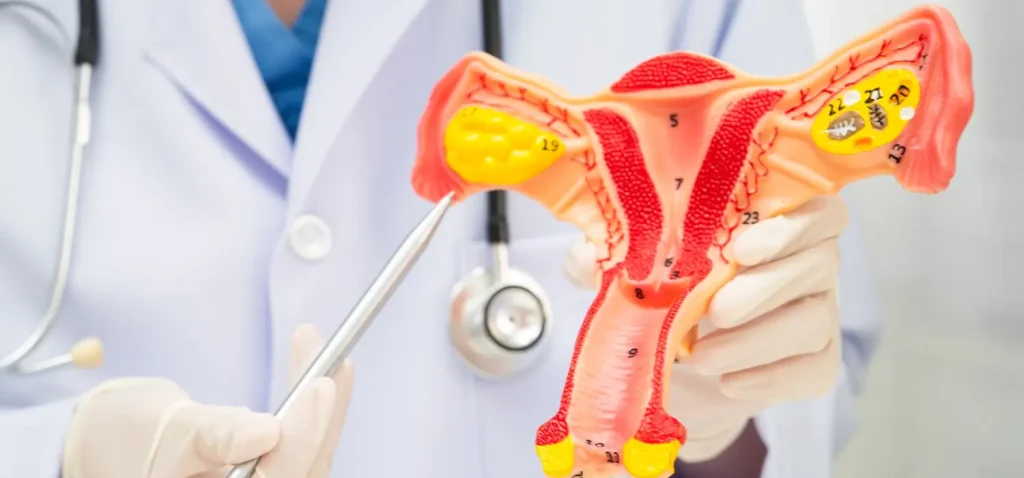
An arcuate uterus is a uterine shape variation in which the upper part of the uterine cavity has a small, shallow indentation. Instead of having a completely smooth, rounded upper cavity, the uterus has a slight dip at the top. The uterus is a hollow, muscular organ where a pregnancy develops. Its shape can vary from one woman to another, and not every variation indicates a medical problem.
An arcuate uterus is generally considered a mild anatomical variation and is often treated as a normal variant in modern clinical classification systems. In most cases, it does not require treatment and does not significantly affect a woman’s ability to conceive or carry a pregnancy.
However, it is important to distinguish an arcuate uterus from other uterine abnormalities, particularly a septate uterus. These conditions can look similar on some scans but may have different implications for reproductive health.
An arcuate uterus develops during the formation of the reproductive organs before birth. During fetal development, the uterus forms through the growth and joining of two structures called the Müllerian ducts. The internal shape of the uterus develops as these structures form and remodel. When the upper portion of the uterine cavity retains a small indentation, the resulting shape may be described as an arcuate uterus.
This is a congenital variation, meaning a woman is born with it. It is not caused by lifestyle choices, sexual activity, contraception, exercise, or anything a woman does during adulthood. There is generally no known way to prevent this variation. It may remain unnoticed throughout life and only be identified during an ultrasound or fertility assessment.
Most women with an arcuate uterus do not experience any symptoms directly related to the uterine shape. Many discover it incidentally during a pelvic ultrasound, an investigation for fertility concerns, or an examination during pregnancy.
An arcuate uterus does not usually cause:
If you experience any of these symptoms, they should not automatically be attributed to an arcuate uterus. Other conditions, including endometriosis, fibroids, adenomyosis, hormonal imbalances, or pelvic infections, may need to be considered. A gynecologist can assess your symptoms, medical history, and examination findings to determine whether further investigation is necessary.
An arcuate uterus and a septate uterus both involve an indentation or partition affecting the uterine cavity. However, the depth and configuration of the indentation help distinguish them. An arcuate uterus typically has a shallow, broad indentation at the top of the cavity. A septate uterus has a more substantial internal partition, known as a septum, extending into the uterine cavity.
This distinction matters because a septate uterus has been associated with certain reproductive complications, including miscarriage. An arcuate uterus, on the other hand, is generally considered a minor anatomical variation, and its reproductive significance is usually limited.
A routine two-dimensional ultrasound may not always provide enough information to classify the uterine shape accurately. A three-dimensional transvaginal ultrasound or, in selected cases, magnetic resonance imaging (MRI) may help clarify the anatomy. It is important not to assume that an arcuate uterus is a septate uterus based on a brief scan report alone. The diagnosis should be interpreted by a qualified clinician using appropriate imaging criteria.
For most women, an arcuate uterus does not prevent natural conception. The shallow indentation generally does not significantly interfere with sperm reaching the fallopian tubes, fertilizations, or implantation. If you have been diagnosed with an arcuate uterus and are trying to conceive, the finding alone does not mean you will experience infertility.
When pregnancy does not occur, a complete fertility assessment may consider several factors, including:
The uterine shape should be considered in the context of the overall clinical picture rather than assumed to be the cause of difficulty conceiving. If you have been trying to become pregnant for 12 months without success and are under 35, a fertility evaluation is generally recommended. If you are 35 or older, seek assessment after six months. Earlier evaluation may be appropriate if you have irregular or absent periods, a known reproductive condition, or other risk factors.
Most women with an arcuate uterus can have healthy pregnancies and deliver without complications related to the uterine shape. Research on the association between arcuate uterus and adverse pregnancy outcomes has produced mixed findings. Some studies have explored possible links with miscarriage, preterm birth, or other complications, but the evidence is limited and does not establish that an arcuate uterus consistently causes these outcomes. A diagnosis should therefore not be treated as a prediction that a pregnancy will be high risk.
Your pregnancy care may depend on your obstetric history, the accuracy of the diagnosis, any other medical conditions, and your clinician’s assessment. If you have experienced previous pregnancy losses or preterm births, your doctor may recommend an individualized monitoring plan.
During pregnancy, attend routine antenatal appointments and report any concerning symptoms promptly. Vaginal bleeding, severe abdominal pain, fluid leakage, or other acute symptoms require timely medical assessment regardless of whether you have an arcuate uterus.
An arcuate uterus is usually identified through imaging rather than symptoms. The choice of investigation depends on why the uterine shape is being assessed and what earlier scans have shown.
Transvaginal ultrasound: This scan provides detailed images of the uterus and is often used during gynaecological assessments. Three-dimensional ultrasound can be particularly useful for evaluating the shape of the uterine cavity and the outer contour of the uterus.
Pelvic MRI: MRI may be recommended when ultrasound findings are unclear or when the clinician needs more detailed information about the uterine anatomy.
Hysteroscopy: This procedure uses a thin instrument with a camera to examine the inside of the uterus. It can help assess the uterine cavity, but it does not independently show the external uterine contour. Therefore, it may not be sufficient on its own to distinguish all uterine shape variations.
Not every woman requires additional imaging. If an arcuate uterus is identified incidentally and there are no symptoms or relevant reproductive concerns, your doctor may determine that further investigation is unnecessary.
In most cases, an arcuate uterus does not require treatment. Because it is generally considered a mild anatomical variation, surgery is not routinely recommended simply to change the shape of the uterine cavity. Surgical treatment intended to correct a uterine septum should not automatically be applied to an arcuate uterus. These are different findings, and unnecessary procedures can expose patients to risks without a clear benefit.
If you have experienced recurrent pregnancy loss, infertility, or other reproductive complications, your gynecologist may recommend reviewing the original imaging to confirm the diagnosis and assess for other possible causes. Treatment, if any, should be based on the confirmed condition and your individual medical history rather than the word “arcuate” on an ultrasound report.
An arcuate uterus discovered incidentally may not require urgent attention. However, discussing the finding with a gynecologist can help you understand its significance and whether any follow-up is needed.
Consider booking an appointment if:
Your doctor can review the scan report, explain the findings, and recommend further assessment only when appropriate.
Usually, no. An arcuate uterus is generally considered a mild variation in uterine shape rather than a serious reproductive disorder. Its significance depends on the accuracy of the diagnosis and the woman’s clinical history.
Yes. Most women with an arcuate uterus can conceive naturally. If conception is difficult, other fertility factors should be assessed instead of assuming the uterine shape is responsible.
The available evidence is inconsistent, and an arcuate uterus has not been established as a consistent cause of miscarriage. Women with recurrent pregnancy loss should receive an appropriate evaluation to identify possible contributing factors.
An arcuate uterus is not generally considered a major cause of breech presentation. A baby’s position can be influenced by several factors, and the position should be assessed during routine antenatal care.
Usually not. Surgery is not routinely recommended for an arcuate uterus. If imaging suggests a septate uterus or another uterine abnormality, a specialist should confirm the diagnosis and discuss whether any treatment is appropriate.
Yes. It may be identified during an ultrasound performed before or during pregnancy. However, the degree of detail available depends on the imaging technique and the stage of pregnancy.
Understanding a uterine shape variation can be worrying, particularly if you are planning a pregnancy or have experienced fertility challenges. However, an arcuate uterus does not automatically mean that you will have difficulty conceiving or carrying a pregnancy.
Dr Namrata Jadhav, an experienced and best gynecologist in Dubai with more than 11 years of post-DNB experience, provides personalised gynaecological assessment and guidance based on each woman’s symptoms, reproductive history, and clinical findings.
If your ultrasound report mentions an arcuate uterus, a consultation can help clarify whether the finding is a normal variation or whether further evaluation is needed. Women looking for the best female gynecologist in Dubai should prioritise clear communication, evidence-based advice, and a care plan suited to their individual needs.
An arcuate uterus is a mild variation in uterine shape that is often discovered during routine imaging. For most women, it does not significantly affect fertility or pregnancy outcomes, and treatment is usually unnecessary. The most important step is ensuring that the uterine shape has been correctly identified, especially when fertility concerns or previous pregnancy complications are present. With appropriate assessment and individualized guidance, you can make informed decisions about your reproductive health and pregnancy planning.